

In combination with fulvestrant for patients with HR+/HER2− aBC or mBC with PIK3CA, AKT1, or PTEN alterations following progression on or after ET ± CDK4/6i1
In combination with fulvestrant for patients with HR+/HER2− aBC or mBC with PIK3CA, AKT1, or PTEN alterations following progression on or after ET ± CDK4/6i1
Select patients based on FDA-approved tests for detection of PIK3CA, AKT1, and PTEN.
Dosing Schedule
In combination with fulvestrant,
Benefit-risk balance achieved with 4 days on, 3 days off, every week1
The recommended dose of TRUQAP is 400 mg taken orally twice daily, approximately 12 hours apart, 4 consecutive days on, 3 days off, every week


Graphic illustrating the dosing schedule for TRUQAP and fulvestrant combination therapy. TRUQAP dosing: 200 mg x2 doses, AM and PM, on Days 1-4, with no doses on Days 5-7. Fulvestrant dosing: 500-mg injections on Day 1 and Day 15 of Cycle 1, then Day 1 following 28-day cycles.
Select patients based on an FDA-approved test for detection of PIK3CA, AKT1, and PTEN alterations.
Evaluate FG and HbA1C prior to starting TRUQAP and at regular intervals during treatment. Verify pregnancy status of females of reproductive potential prior to initiating TRUQAP.
See the full TRUQAP Prescribing Information for additional information related to hyperglycemia.
Advise patients on the following when taking TRUQAP:

Can be taken with or
without food

Swallow whole

Do not chew, crush, or split tablets prior to swallowing. Do not take tablets that are broken, cracked, or otherwise not intact

Do not consume
grapefruit products

If a patient misses a dose within 4 hours of the scheduled time, instruct the patient to take the missed dose. If a patient misses a dose by more than 4 hours of the scheduled time, instruct the patient to skip the dose and take the next dose at its usual scheduled time

If a patient vomits a dose, instruct the patient not to take an additional dose and to take the next dose at its usual scheduled time

For pre-/perimenopausal women, administer an LHRH agonist according to current clinical practice standards. For men, consider administering an LHRH agonist according to current clinical practice standards
Continue treatment until disease progression or unacceptable toxicity occurs.
Evaluate FG and HbA1C prior to starting TRUQAP and at regular intervals during treatment. Verify pregnancy status of females of reproductive potential prior to initiating TRUQAP.
Can be taken with or without food
Swallow whole with water
Do not chew, crush, or split tablets prior to swallowing. Do not take tablets that are broken, cracked, or otherwise not intact
Do not consume
grapefruit products
If a patient misses a dose within 4 hours of the scheduled time, instruct the patient to take the missed dose. If a patient misses a dose by more than 4 hours of the scheduled time, instruct the patient to skip the dose and take the next dose at its usual scheduled time
If a patient vomits a dose, instruct the patient not to take an additional dose and to take the next dose at its usual scheduled time
For pre-/perimenopausal women, administer an LHRH agonist according to current clinical practice standards. For men, consider administering an LHRH agonist according to current clinical practice standards
Continue treatment until disease progression or unacceptable toxicity occurs.
Evaluate FG and HbA1C prior to starting TRUQAP and at regular intervals during treatment. Verify pregnancy status of females of reproductive potential prior to initiating TRUQAP.
Blister packs help patients on TRUQAP track their doses1
Designed to help patients follow their medication schedule.


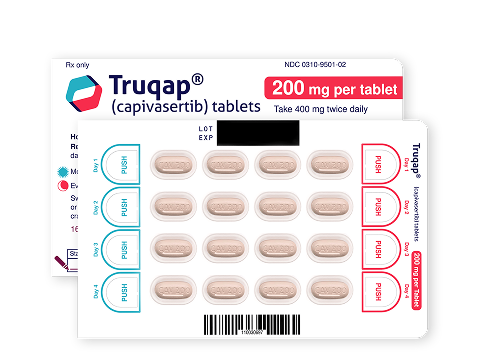
400 mg twice daily
Two 200-mg tablets BID
NDC 0310-9501-02
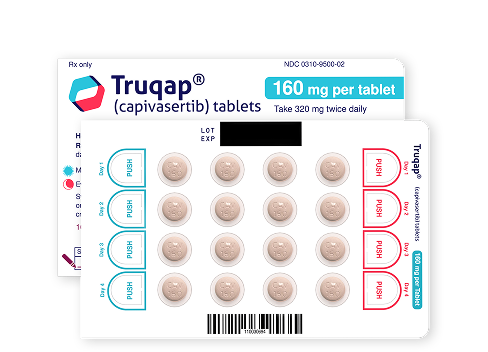
320 mg twice daily
Two 160-mg tablets BID
NDC 0310-9500-02
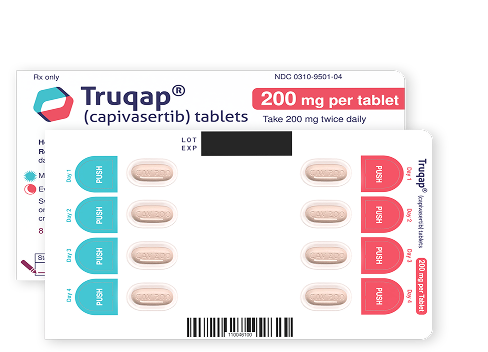
200 mg twice daily
One 200-mg tablet BID
NDC 0310-9501-04
In combination with fulvestrant,
In the event of a dose reduction, the dosing schedule remains the same: 4 consecutive days on, 3 days off, every week
First dose reduction
320 mg twice daily for 4 consecutive days followed by 3 days off

Two 160-mg tablets BID
Not actual size.
Second dose reduction
200 mg twice daily for 4 consecutive days followed by 3 days off

One 200-mg tablet BID
Not actual size.
TRUQAP dose modifications by AR
FG >ULN-160 mg/dL
or
FG >ULN-8.9 mmol/L
or
HbA1C >7%
FG 161-250 mg/dL
or
FG 9-13.9 mmol/L
FG 251-500 mg/dL
or
FG 14-27.8 mmol/L
FG >500 mg/dL
or
FG >27.8 mmol/L
or
life-threatening sequelae of hyperglycemia at any FG level
Grade 2
Grade 3
Grade 4
Grade 2
Grade 3
Grade 4
Grade 2
Grade 3
Grade 4
Discover TRUQAP
tolerability profile
Find support for patients
aBC=locally advanced breast cancer not amenable to resection or radiation therapy with curative intent; AKT1=serine/threonine protein kinase 1; AR=adverse reaction; CDK4/6i=cyclin-dependent kinase 4/6 inhibitor; CTCAE=Common Terminology Criteria for Adverse Events; ET=endocrine therapy; FG=fasting glucose; HbA1C=glycated hemoglobin; HER2−=human epidermal growth factor receptor 2 negative; HR+=hormone receptor positive; LHRH=luteinizing hormone-releasing hormone; mBC=metastatic breast cancer; PIK3CA=phosphatidylinositol-4,5-bisphosphate 3-kinase catalytic subunit alpha; PTEN=phosphatase and tensin homolog; ULN=upper limit of normal.
References: 1. TRUQAP® (capivasertib) [prescribing information]. Wilmington, DE: AstraZeneca Pharmaceuticals LP; 2026. 2. Miller C, Sommavilla R, Murphy D, Morris T, Khatun M, Cullberg M. The effect of food and acid-reducing agents on the pharmacokinetic profile of capivasertib: results from a randomized, crossover study. Br J Clin Pharmacol. 2023;89(11):3330-3339. doi:10.1111/bcp.15831 3. Turner NC, Oliveira M, Howell SJ, et al. Capivasertib in hormone receptor–positive advanced breast cancer. N Engl J Med. 2023;388(22):2058-2070. doi:10.1056/NEJMoa2214131

IMPORTANT SAFETY INFORMATION ABOUT TRUQAP® (capivasertib) tablets
TRUQAP is contraindicated in patients with severe hypersensitivity to TRUQAP or any of its components.
Hyperglycemia
TRUQAP can cause severe hyperglycemia, including diabetic ketoacidosis and fatal outcomes
Metastatic HR-Positive, HER2-Negative Breast Cancer
PTEN-Deficient Metastatic Androgen Pathway Modulation-Naïve or -Sensitive Prostate Cancer
The safety of TRUQAP has not been established in patients with Type 1 diabetes or Type 2 diabetes that is uncontrolled or requiring insulin at baseline as these patients were excluded from clinical studies. Before initiating treatment with TRUQAP, test fasting glucose levels (FPG or FBG), HbA1C levels, and optimize fasting glucose. After initiating treatment with TRUQAP, monitor or self-monitor FG levels on Day 3 or 4 of the dosing week during weeks 1, 2, 4, 6, and 8; then monthly while on treatment with TRUQAP; and as clinically indicated. Monitor HbA1C levels every 3 months during treatment with TRUQAP and as clinically indicated. Patients with a history of well-controlled Type 2 diabetes mellitus may require intensified anti-hyperglycemic treatment and close monitoring of FG levels.
For patients who experience hyperglycemia during treatment with TRUQAP, monitor FG at least twice weekly, on days on and off TRUQAP, until FG decreases to baseline levels. During treatment with anti-diabetic medications, monitor FG at least once a week for 2 months, followed by once every 2 weeks, or as clinically indicated. Consider consultation with a healthcare practitioner with expertise in the treatment of hyperglycemia and initiation of FG monitoring at home for patients who have risk factors for hyperglycemia or who experience hyperglycemia. Advise patients on the signs and symptoms of hyperglycemia and counsel patients on lifestyle changes.
Withhold TRUQAP immediately when ketoacidosis is suspected. If ketoacidosis is confirmed, permanently discontinue TRUQAP. Withhold TRUQAP in clinical situations known to increase the risk of severe hyperglycemia or ketoacidosis (eg, suspected serious infection or acute illness). Based on the severity of hyperglycemia, withhold, reduce dose, or permanently discontinue TRUQAP.
Diarrhea
TRUQAP can cause severe diarrhea associated with dehydration
Metastatic HR-Positive, HER2-Negative Breast Cancer
PTEN-Deficient Metastatic Androgen Pathway Modulation-Naïve or -Sensitive Prostate Cancer
Monitor patients for signs and symptoms of diarrhea. Advise patients to increase oral fluids and start anti-diarrheal treatment at the first sign of diarrhea while taking TRUQAP. Withhold, reduce dose, or permanently discontinue TRUQAP based on severity.
Cutaneous Adverse Reactions
TRUQAP can cause cutaneous adverse reactions, which can be severe, including erythema multiforme (EM), palmar-plantar erythrodysesthesia (PPE), and drug reaction with eosinophilia and systemic symptoms (DRESS).
Metastatic HR-Positive, HER2-Negative Breast Cancer
PTEN-Deficient Metastatic Androgen Pathway Modulation-Naïve or -Sensitive Prostate Cancer
Monitor patients for signs and symptoms of cutaneous adverse reactions. Early consultation with a dermatologist is recommended. Withhold, reduce dose, or permanently discontinue TRUQAP based on severity.
Embryo-Fetal Toxicity
Based on findings from animals and mechanism of action, TRUQAP can cause fetal harm when administered to a pregnant woman. Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment with TRUQAP and for
1 month after the last dose.
Advise male patients with female partners of reproductive potential to use effective contraception during treatment with TRUQAP and for 4 months after the last dose.
TRUQAP is used in combination with fulvestrant or abiraterone. Refer to the full Prescribing Information of fulvestrant or abiraterone for pregnancy and contraception information.
ADVERSE REACTIONS
Metastatic HR-Positive, HER2-Negative Breast Cancer
PTEN-Deficient Metastatic Androgen Pathway Modulation-Naïve or -Sensitive Prostate Cancer
DRUG INTERACTIONS
Strong CYP3A Inhibitors: Avoid concomitant use with a strong CYP3A inhibitor. If concomitant use cannot be avoided, reduce the dose of TRUQAP and monitor patients for adverse reactions.
Moderate CYP3A Inhibitors: When concomitantly used with a moderate CYP3A inhibitor, reduce the dose of TRUQAP and monitor patients for adverse reactions.
Strong or Moderate CYP3A Inducers: Avoid concomitant use of TRUQAP with strong or moderate CYP3A inducers.
INDICATIONS AND USAGE
Please see full Prescribing Information, including Patient Information for TRUQAP.
You may report side effects related
to AstraZeneca products .
INDICATIONS AND USAGE
IMPORTANT SAFETY INFORMATION ABOUT TRUQAP™ (capivasertib) tablets
Expand

